How big is the cell therapy market really?
Building a startup or looking for your next investment in cell therapy? Our report gives you the full picture.
Summary
The cell therapy market is currently around $9 billion to $10 billion in annual therapeutic-product sales, with roughly $8 billion to $12 billion as the range we would trust today.
The huge spread in published estimates is mostly a definition problem. A $6 billion market focused on proprietary cell medicines and an $18 billion market that pulls in broader stem-cell activity are not measuring the same revenue pool.
The strongest anchor is bottom-up product revenue. Nine identifiable therapies generated about $3.61 billion in the latest six-month period, implying a rough annual run rate above $7.2 billion before Abecma, Ryoncil, Epicel, Provenge, Tecelra, regional products and smaller franchises are added.
CAR-T still dominates the business in dollars. It represented about 89% of the nine-product basket, but Amtagvi, Casgevy, MACI and Ryoncil show that commercial cell therapy is finally broadening beyond the original blood-cancer CAR-T model.
Revenue makes the market look bigger than its patient reach. At roughly $500,000 of product revenue per treatment, $10 billion of sales corresponds to only about 20,000 treatment equivalents, so the industry can become much larger simply by treating more patients even if average prices eventually fall.
Growth is real, but it is very uneven. Carvykti and Breyanzi are expanding quickly while older CAR-T products are losing sales, and newer modalities are growing from much smaller bases.
Solid tumors have crossed from pipeline story to commercial reality, but they remain tiny beside hematology. Amtagvi is already meaningful revenue, while satri-cel shows engineered CAR-T can also reach approval in a solid tumor.
The upside case has become less clean. Autoimmune CAR-T now carries fresh safety questions, several allogeneic CAR-T programs have been abandoned, and the industry is learning that clinical promise does not automatically translate into a scalable commercial category.
Manufacturing is no longer the only bottleneck. Production success rates, turnaround times and regulatory logistics have improved, while treatment-center capacity, insurance approval, collection, conditioning, infusion and monitoring increasingly determine how many patients can actually be treated.
The pipeline is still unusually large relative to the commercial base: 618 active cell-therapy trials, including 302 already in Phase II or later. A roughly $15 billion to $25 billion market around 2030 looks achievable without heroic assumptions; $50 billion becomes realistic if several larger indications work, while $100 billion still requires multiple major breakthroughs to succeed at the same time.

Written by the New Market Pitch teamWe track new markets so founders and investors can move faster. About us

In our report covering the cell therapy market, we always try to gather several sources and make estimates that make sense, so you can work with solid numbers.
Why do cell therapy market estimates differ by more than $10 billion?
The cell therapy market has no single trustworthy published size today because different researchers are counting very different things.
The spread is hard to ignore. Mordor Intelligence currently puts the market at $6.55 billion. Towards Healthcare says $8.85 billion. Fortune Business Insights says $12.22 billion. IMARC starts from $18 billion in 2025. Grand View Research's older model sits closer to $6 billion.
A $6 billion market and an $18 billion market cannot both describe the same pool of drug sales.
The definitions explain much of the gap. Fortune's latest report is overwhelmingly about commercial CAR-T products and says CAR-T represented 99.8% of its 2025 market. IMARC includes stem-cell therapies across musculoskeletal disorders, dermatology, malignancies and other uses, with hospitals, clinics and research institutes all inside its scope. Other reports mix proprietary therapies with parts of regenerative medicine that behave more like medical procedures.
There is another source of confusion. Cell-therapy manufacturing, reagents, instruments, CDMO work and software are themselves multibillion-dollar markets. Those companies benefit from cell therapy, but adding their revenue to the sales of the medicines creates an ecosystem number rather than a drug-market number.
So before asking whether cell therapy is a $6 billion, $10 billion or $18 billion market, we first need to decide what we are actually measuring.
What should actually count as the cell therapy market?
For a useful commercial estimate, the cell therapy market should count sales of approved treatments in which living cells are the therapeutic product given to the patient.
That includes autologous CAR-T, TIL and TCR therapies, donor-derived cellular medicines, cultured cell products and ex vivo gene-edited cells. Casgevy belongs in this group even though people frequently call it a gene therapy: Vertex describes Casgevy as an ex vivo CRISPR-edited cell therapy, and the medicine ultimately infused into the patient consists of modified living stem cells.
We would keep conventional stem-cell transplantation separate. A bone-marrow transplant is clearly a cell therapy medically, but most of the money around transplantation comes from hospitals, donor procurement, conditioning, collection, laboratory work and clinical care. Treating all of that as product revenue makes comparisons with drugs such as Carvykti or Amtagvi almost meaningless.
We would also keep manufacturing equipment, culture media, CDMO revenue and research tools outside the core number. They belong to the broader cell-therapy economy, which is worth substantially more.
| Category | Count in core market? | Why |
|---|---|---|
| Autologous CAR-T | Yes | Living engineered cells are the medicine |
| TIL and TCR therapies | Yes | Living therapeutic immune cells |
| Ex vivo gene-edited cell therapies | Yes | Modified cells are infused as the product |
| Allogeneic cell therapies | Yes | Donor-derived living cells are the medicine |
| Cultured regenerative cell products | Yes | Therapeutic product consists of living cells |
| Conventional stem-cell transplantation | Separate | Economics are dominated by procedure and hospital care |
| Cell-therapy manufacturing services | No | Supplier revenue rather than therapy sales |
| Reagents, instruments and research tools | No | Part of the supporting ecosystem |
| In vivo gene therapies | No | No therapeutic cells are manufactured and reinfused |
If you want more recent data on this point, please see our latest cell therapy market report.

Theory only gets you so far. In our research about cell therapies, we dig up the real signals from the field and show you the ones worth watching.
How much are approved cell therapies actually selling today?
Approved cell therapies are currently generating around $9 billion to $10 billion a year in product revenue, with roughly $8 billion to $12 billion as the range we can defend from observable sales.
We can get surprisingly close without trusting any market-research estimate.
The latest first-half company disclosures show $1.25 billion from Carvykti, $896 million from Breyanzi, $679 million from Yescarta, $146 million from Tecartus and $169 million from Kymriah. Outside those established CAR-T franchises, Amtagvi produced $151 million, MACI $122 million, Casgevy $119 million and Aucatzyl almost $72 million.
Those nine products alone generated about $3.61 billion in six months, which translates to a rough annual run rate above $7.2 billion.
And that basket is incomplete. It leaves out Abecma, Ryoncil, Epicel, Provenge, Tecelra, newer products, therapies sold primarily in Asia and several smaller cellular medicines. Ryoncil, for example, reached $115 million in its first full commercial year.
That makes a global therapeutic cell-therapy market of only $5 billion to $6 billion very hard to reconcile with the sales companies are already reporting. Getting to $18 billion, on the other hand, requires a broader definition that includes more stem-cell activity, services or other adjacent revenue.
Around $9 billion to $10 billion is the number that best fits the commercial evidence today.
| Therapy | Latest first-half sales | Change vs. previous year | Type |
|---|---|---|---|
| Carvykti | $1.254B | +55% | Autologous CAR-T |
| Breyanzi | $896M | +48% | Autologous CAR-T |
| Yescarta | $679M | -13% | Autologous CAR-T |
| Kymriah | $169M | -15% | Autologous CAR-T |
| Amtagvi | $151M | +55% | Autologous TIL |
| Tecartus | $146M | -15% | Autologous CAR-T |
| MACI | $122M | +22% | Cultured autologous cells |
| Casgevy | $119M | +167% | Gene-edited autologous cells |
| Aucatzyl | $72M | +140% | Autologous CAR-T |
Is CAR-T still basically the whole cell therapy market?
CAR-T still makes most of the money in cell therapy today, even though other types of cell therapy are finally becoming commercially visible.
In the nine-product basket above, CAR-T generated about $3.22 billion of the $3.61 billion total. That is roughly 89%.
The true global percentage will be somewhat lower once we add regenerative therapies, donor-derived products and smaller regional products, but there is no realistic calculation where CAR-T suddenly becomes a minority of current commercial revenue.
That concentration says a lot about the maturity of the market. The industry may contain hundreds of technologies and companies, yet a handful of personalized cancer treatments still generate most of the actual sales.
The interesting change is happening below that top layer. Amtagvi has turned TIL therapy into a real commercial category. Casgevy is creating meaningful revenue from CRISPR-edited stem cells. MACI is approaching a $300 million annual revenue run rate in cartilage repair. Ryoncil generated more than $100 million during its first full commercial year as an allogeneic mesenchymal stromal-cell therapy.
Cell therapy is still mostly CAR-T in dollars, but there is finally enough revenue outside CAR-T to see the beginnings of a broader market.

In our market report about cell therapies, we don't want to repeat what boring consulting reports say. Instead, we show you the real and latest market signals that matter.
Is the cell therapy market really growing, or are new CAR-T drugs just replacing old ones?
Cell therapy is genuinely growing, although today's CAR-T market is already splitting sharply between winners and losers.
Carvykti and Breyanzi are doing most of the heavy lifting among established CAR-T products. Their combined first-half sales increased by roughly $735 million from the previous year.
Over the same period, Gilead's Yescarta and Tecartus franchise lost about $125 million, while Kymriah lost another $30 million. Abecma has also been under competitive pressure.
That means the category can grow quickly while several individual therapies shrink at double-digit rates.
The younger products show a different pattern. Amtagvi grew 55%, Casgevy 167%, Aucatzyl 140% and MACI 22%. Together, those four products went from roughly $272 million to $464 million in first-half sales, an increase of about 71%.
So applying one CAGR to "cell therapy" is pretty crude. The market contains mature products losing share, blockbuster products still scaling rapidly, and entirely new cell-therapy categories growing from tiny bases.
It looks more like the early years of a pharmaceutical platform than one homogeneous market moving up a clean growth curve.
If you want more recent data on this point, please see our latest cell therapy market report.
How can cell therapy already produce blockbuster drugs with so few patients?
Cell therapy can generate blockbuster revenue from surprisingly few patients because revenue per treatment is enormous.
Most established U.S. CAR-T therapies carry list prices around half a million dollars per infusion. Casgevy's U.S. list price is about $2.2 million. Realized manufacturer revenue is lower after discounts and other adjustments, but the basic arithmetic remains extreme.
At $500,000 of product revenue per treatment, $10 billion of sales corresponds to only about 20,000 treatment equivalents.
That is tiny beside pharmaceutical categories where millions of people take the same medicine every day.
A $10 billion cell-therapy market can therefore look substantial in revenue terms while patient penetration remains very low.
Future growth does not require prices to keep rising. If manufacturing and treatment capacity improve enough for the industry to treat 50,000, 100,000 or 200,000 patients a year, the revenue opportunity becomes much larger even at lower average prices.
Are cell therapies still mostly blood-cancer treatments?
Cell therapy revenue is still heavily tied to blood cancer today, but the first serious businesses outside hematology are already here.
The biggest commercial products remain concentrated in multiple myeloma, lymphoma and leukemia. That is why cell therapy can still feel almost synonymous with CAR-T oncology.
Outside those cancers, the commercial list is now much harder to dismiss.
Amtagvi treats advanced melanoma and is already producing close to $100 million in a quarter. Casgevy treats sickle cell disease and transfusion-dependent beta thalassemia. MACI treats cartilage defects in the knee. Ryoncil is used for steroid-refractory acute graft-versus-host disease in children. Epicel is used in severe burns.
Asia is widening the map further. Japan has recently approved cell therapies involving iPS-derived cells for Parkinson's disease and severe heart failure, while additional regenerative products have reached the market in orthopedics and dermatology.
None of those categories rivals blood-cancer CAR-T revenue yet.
Still, today's cell therapy market has clearly moved beyond one disease area. If even two or three of these newer indications create billion-dollar products, the composition of the market changes quickly.

In our document detailing everything you need to know about cell therapy, we like to show you the big picture. We know your time is precious, so we make every page quick to read and packed with as much learning as possible per minute.
Are solid tumors finally becoming a real cell therapy market?
Solid-tumor cell therapy is commercially real now, although it remains small beside blood-cancer CAR-T.
Amtagvi provides the clearest proof. Iovance's TIL therapy for advanced melanoma generated $151 million during the first half and $91 million in its latest quarter. That is already large enough to move beyond the "interesting clinical experiment" stage.
China added another important step when regulators approved satri-cel for CLDN18.2-positive advanced gastric or gastroesophageal cancer. It became the world's first approved CAR-T therapy specifically for a solid tumor.
Those two products attack solid tumors in very different ways. TIL therapy has demonstrated that patient-derived immune cells can become a commercial solid-tumor treatment, while satri-cel shows that engineered CAR-T can also cross the regulatory line.
The revenue gap with hematology remains huge. One leading blood-cancer CAR-T can currently generate more in a quarter than the entire commercial solid-tumor cell-therapy category.
Solid tumors have crossed the commercial starting line. The real expansion comes later if similar results become repeatable in common cancers such as lung, colorectal, pancreatic, breast or ovarian cancer.
Could autoimmune disease become the next huge cell therapy market?
Autoimmune disease could become one of the biggest new markets for cell therapy, but the opportunity looks much less de-risked today than it did only recently.
The attraction is obvious. Severe lupus, systemic sclerosis, myositis, rheumatoid arthritis and multiple sclerosis together expose cell therapy to patient populations far larger than the refractory blood-cancer niches that created the first CAR-T blockbusters.
The early efficacy data have also been difficult to ignore. Cabaletta recently presented results from 52 evaluable patients treated with rese-cel across myositis, lupus and systemic sclerosis. Among six dermatomyositis patients in one cohort, five reached an immunomodulator-free moderate-to-major response at 16 weeks, with those responses maintained through the available follow-up.
Then came a major safety warning.
Novartis recently paused eight trials of rapcabtagene autoleucel across autoimmune and neurological diseases after three patients died from complications linked to a severe immune reaction known as IEC-HS. Bristol Myers Squibb also paused autoimmune studies of its competing CAR-T program while reviewing safety events.
That changes how aggressively we should size the opportunity. Developers now have to show that the risk-benefit profile works in patients who often have other treatment options and may live for decades with their disease.
Autoimmune CAR-T still has enormous commercial potential. Today, however, it belongs in the upside case rather than in the revenue base we can confidently forecast.
If you want more recent data on this point, please see our latest cell therapy market report.

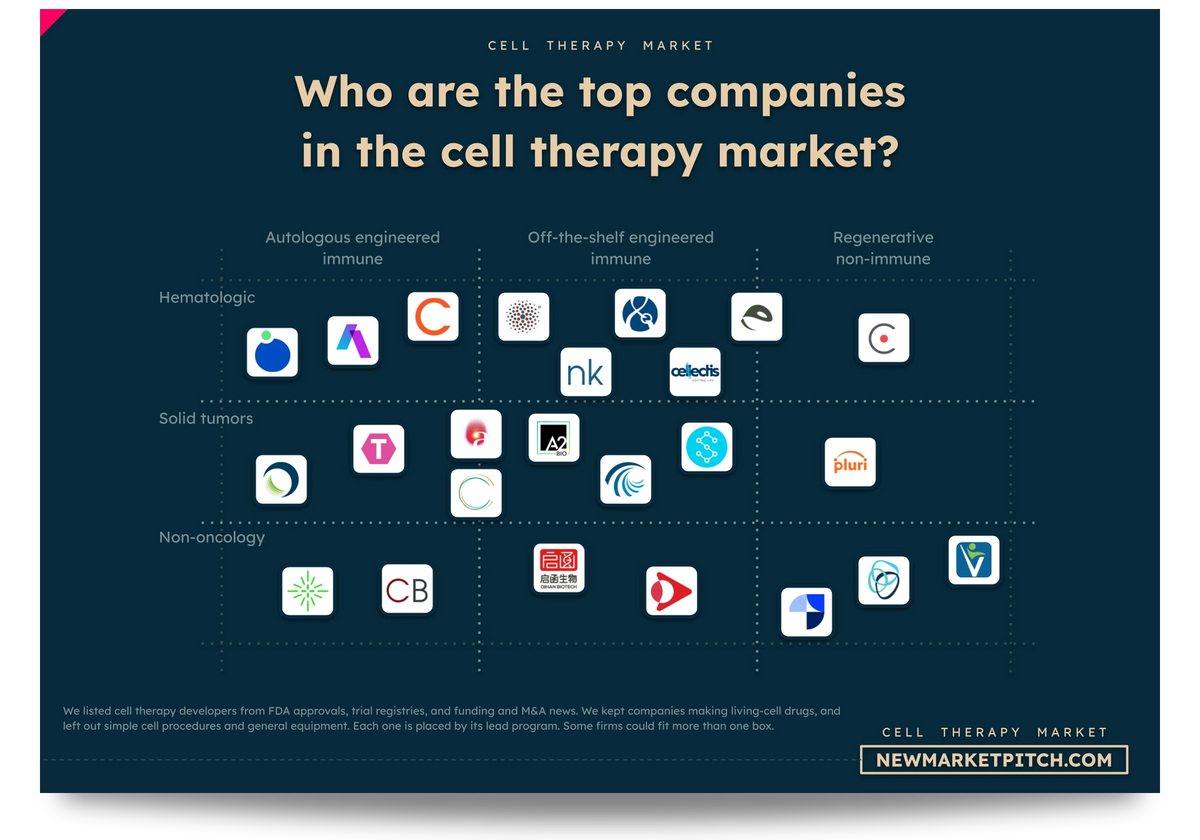
In our report covering the cell therapy market, we turn what is vague and complex into simple, useful visuals. Market maps like this one show you at a glance where every startup stands.
Is off-the-shelf cell therapy finally working?
Off-the-shelf cell therapy already works as a commercial concept, while off-the-shelf CAR-T is still struggling to prove that it can beat personalized CAR-T.
Ryoncil is an important example. The therapy uses donor-derived mesenchymal stromal cells and produced roughly $115 million during its first full commercial year. Tregzi adds another donor-derived cellular product to the U.S. market around stem-cell transplantation.
The harder question concerns allogeneic CAR-T. For years, the pitch was compelling: manufacture large batches from healthy donors, store them, and treat patients immediately instead of building a new product for each individual.
The clinical progress has been much slower than the promise.
Sana suspended two allogeneic CAR-T programs in late 2025. More recently, Cellectis made an even sharper move. At the beginning of 2026, Cellectis was still describing itself as a late-stage allogeneic CAR-T company and was running a pivotal trial of lasme-cel. The company has now decided to exit development of lasme-cel and eti-cel after concluding that smaller addressable patient populations, bispecific antibodies and rapidly emerging in vivo CAR-T approaches had weakened the commercial case.
That reversal within the same year says more than another preclinical announcement would.
Off-the-shelf cells can become real medicines. What we still do not know is whether donor-derived CAR-T can become the cheaper, easier successor to today's autologous products.
Is manufacturing still the main thing holding cell therapy back?
Manufacturing is still expensive and complicated, but access to treatment centers and the overall care pathway now look just as important.
The industry has solved a lot of the early production problems. Large CAR-T manufacturers now report far better manufacturing success rates, more predictable turnaround times and much larger networks of qualified treatment sites.
Regulation has also become easier operationally. The FDA removed the REMS programs for the six established CD19- and BCMA-directed autologous CAR-T therapies in 2025. Hospitals no longer have to participate in the same special certification system, and some monitoring requirements were shortened.
Commercial manufacturers are also learning how to make these products more efficiently. Iovance reported a 56% gross margin in its latest quarter as Amtagvi volumes increased and its internal manufacturing network became better utilized. Autolus reported improving economics for Aucatzyl as production volumes increased.
But patients still need collection, scheduling, specialist physicians, insurance approval, conditioning in many cases, infusion and close monitoring. Treatment often happens at a limited number of experienced centers.
So the factory is only one part of the bottleneck now. The harder scaling problem is getting the whole healthcare system around the factory to handle far more patients.
If you want more recent data on this point, please see our latest cell therapy market report.

Our research about cell therapies gets updated several times a month, so you always get the latest view of where things stand.
Should normal stem-cell transplants count in the cell therapy market?
Stem-cell transplantation should be tracked alongside cell therapy, but counting the entire transplant economy inside the drug market would inflate the number badly.
The treatment volume is already much larger than modern CAR-T.
The European Society for Blood and Marrow Transplantation recorded 47,204 hematopoietic cell transplants in 43,791 patients across 688 centers in its latest full activity report. In the same network, CAR-T treatment reached 6,082 patients.
That gives conventional transplantation roughly eight times the treatment volume of CAR-T in the same reporting system.
Yet the economics are completely different. A transplant episode includes donor procurement, cell collection, laboratory processing, conditioning chemotherapy, hospital stays, physicians and supportive care. Much of that revenue goes to providers rather than to the manufacturer of a proprietary medicine.
This is one reason published market estimates can drift so far apart. A researcher who values cellular treatments through hospital activity will get a much bigger number than someone adding pharmaceutical product sales.
For our estimate, conventional transplantation belongs in the wider cell-therapy economy, while the core market remains the sales of commercial cellular medicines.
How much cell therapy is actually coming through the pipeline?
The cell therapy pipeline is huge compared with today's commercial market, with more than 600 active clinical trials and over 300 already in Phase II or later.
The Alliance for Regenerative Medicine's latest detailed dataset counts 618 active cell-therapy trials. That includes 198 in Phase I, 118 in Phase I/II, 222 in Phase II, 17 in Phase II/III and 63 in Phase III.
The late-stage part is more important than the headline total. Phase II, Phase II/III and Phase III together account for 302 trials. We are dealing with hundreds of programs that have moved beyond the earliest human testing.
The disease mix is also broader than today's sales suggest. ARM classifies 347 cell-therapy trials as targeting prevalent diseases, compared with 180 focused on rare diseases and another 91 spanning both. Current revenue is concentrated in relatively small oncology populations, while much of the development pipeline is already aiming at bigger patient groups.
The developer count is even more striking. ARM tracks more than 1,000 companies, institutions and other organizations working on cell therapy globally.
Most of those programs will fail, overlap with one another or never become meaningful products. Still, a market with roughly a dozen important commercial therapies and more than 600 active trials has a lot of shots on goal.
That is the strongest quantitative reason to expect cell therapy revenue to remain a growth market for years.

In our market report about cell therapies, you will always find fresh funding data, taken straight from our own verified funding database.
Could in vivo CAR-T completely change cell therapy economics?
In vivo CAR-T could make cell therapy far easier to scale because it tries to create the engineered cells directly inside the patient.
Traditional CAR-T requires a long chain of steps. Cells leave the patient, travel to a manufacturing site, get engineered and expanded, pass quality control, travel back to the hospital and are finally infused.
In vivo CAR-T tries to deliver the genetic instructions directly into the body and turn the patient's immune cells into CAR-T cells there.
We now have enough human data to take the idea seriously. Legend Biotech recently reported Phase I results for LB2501 in 12 patients with relapsed or refractory B-cell non-Hodgkin lymphoma. Among the six patients at the higher dose, all six responded and five achieved complete responses. The treatment generated CAR-T cells inside patients after a single infusion, without lymphodepleting chemotherapy in the study.
Six patients at one dose is far too small to prove commercial viability. The result is still important because it attacks several of the industry's biggest bottlenecks at once.
If in vivo CAR-T eventually works reliably, the manufacturing model starts looking more like conventional drug production. Waiting times could fall, treatment-center capacity could rise and personalized manufacturing would become much less central.
That would change the size of the market by changing how many patients the industry can physically treat, rather than simply by launching another expensive CAR-T product.
Can cell therapy realistically become a $50 billion or $100 billion market?
A $50 billion cell therapy market is realistic over the longer term, while $100 billion still requires several major new markets to work at the same time.
The lower target does not demand anything absurd.
If our current $8 billion to $12 billion commercial range grows around 15% annually, the market reaches roughly $14 billion to $21 billion after four years. At 20%, it reaches roughly $17 billion to $25 billion. Continued growth beyond that can take the industry toward $50 billion as more indications launch.
Getting to $100 billion is much harder. Today's high-priced blood-cancer model alone probably cannot support that scale.
A market that large would need meaningful revenue from several of the following at once: common solid tumors, autoimmune diseases, regenerative medicine, neurological disease, diabetes or cardiovascular disease. It would also need manufacturing and treatment capacity to support far more patients than the system handles now.
Published forecasts show just how uncertain this is. Recent market reports range from around $12 billion to more than $120 billion in their longer-term estimates.
The lower forecasts underestimate the number of new categories already reaching the clinic. The most aggressive forecasts assume that several of those categories will become enormous commercial businesses before that has been demonstrated.
| Research firm | Current/base estimate | Long-term forecast | What the forecast implies |
|---|---|---|---|
| Expert Market Research | $4.18B in 2024 | $12.08B by 2034 | Slow commercialization |
| TechSci Research | $6.74B in 2025 | $13.32B by 2031 | ~12% annual growth |
| Mordor Intelligence | $6.55B in 2026 | $14.56B by 2031 | ~17% annual growth |
| Grand View Research | ~$5.9B base | $20.07B by 2030 | Strong growth from a narrow base |
| Towards Healthcare | $8.85B in 2026 | $55.72B by 2035 | Multiple new indications succeed |
| IMARC | $18.0B in 2025 | $61.0B by 2034 | Broader market definition |
| Fortune Business Insights | $12.22B in 2026 | $122.87B by 2034 | Cell therapy becomes a mass-scale platform |
If you want more recent data on this point, please see our latest cell therapy market report.

In our document detailing everything you need to know about cell therapy, we look at what the winners do differently, so you can learn from the best instead of guessing.
How big is the cell therapy market really?
The cell therapy market is currently around $9 billion to $10 billion in annual therapeutic-product sales, and roughly $8 billion to $12 billion is the range we would trust today.
As the product revenue work above shows, nine clearly identifiable therapies already generated more than $3.6 billion in only six months. Their rough annualized run rate exceeds $7.2 billion before adding several approved therapies, regional products and smaller franchises.
That bottom-up calculation is much harder to argue with than one market-research CAGR.
The market is also smaller in patient terms than the revenue figure makes it look. High prices allow tens of thousands of treatments to create billions of dollars of sales. CAR-T still generates most of those dollars, and blood cancer remains the commercial center of gravity.
What makes cell therapy unusually interesting is the gap between today's business and today's pipeline. More than 600 cell-therapy trials are active, over 300 are already in Phase II or later, solid-tumor therapies have begun producing commercial revenue, donor-derived cells are reaching patients, and early in vivo CAR-T data suggest that the delivery model itself may eventually change.
There are also fresh reasons to keep the upside under control. Autoimmune CAR-T has just suffered a serious safety setback. Several allogeneic CAR-T programs have been abandoned. Older commercial CAR-T products are already losing sales to newer competitors.
Our judgment is fairly tight: cell therapy is already a real $9 billion to $10 billion pharmaceutical market, a roughly $15 billion to $25 billion market around 2030 looks achievable without heroic assumptions, and $50 billion becomes realistic if cell therapy starts winning in several larger diseases. A $100 billion market remains possible, but today it still depends on multiple breakthroughs that have yet to prove themselves commercially.
Our methodology
This analysis estimates the size of the cell therapy market by separating commercial therapeutic-product revenue from the much wider cell-therapy economy. The core market includes approved treatments in which living cells are the therapeutic product given to the patient, including autologous CAR-T, TIL and TCR therapies, donor-derived cellular medicines, cultured cell products and ex vivo gene-edited cells. Conventional stem-cell transplantation, manufacturing services, CDMO revenue, reagents, instruments and research tools are treated separately.
We did not average published market estimates. We used them to understand how much definitions diverge, then rebuilt the current market from evidence closer to actual commercial activity. Mordor Intelligence, Fortune Business Insights, IMARC and Towards Healthcare are used as examples of published market models with materially different scopes and starting values.
For the current commercial base, we prioritized company-reported product revenue. The bottom-up estimate uses the latest first-half 2026 disclosures available for Carvykti, Breyanzi, Yescarta, Tecartus, Kymriah, Amtagvi, MACI, Casgevy and Aucatzyl, then checks that basket against additional approved products such as Ryoncil and other smaller or regional therapies that are not fully captured in the nine-product total.
For the growth case, we gave more weight to observable commercial and clinical evidence than to long-range market forecasts. Approved products and reported sales belong in the base. Regulatory changes, treatment volumes, Phase II and Phase III pipeline activity, new disease categories and recent program decisions inform the growth case. Early clinical results, including in vivo CAR-T and autoimmune programs, remain upside until larger datasets and commercial evidence appear.
We also distinguish drug revenue from healthcare-system activity. The European Society for Blood and Marrow Transplantation data are used to compare conventional transplant and CAR-T treatment volumes, while the FDA's removal of REMS requirements for established autologous CAR-T therapies informs the discussion of operational access. Alliance for Regenerative Medicine data provide the main pipeline counts, phase distribution, disease mix and developer totals.
Key sources used for this analysis include Mordor Intelligence on the published cell therapy market estimate, Fortune Business Insights on market size, forecast and CAR-T share, IMARC on the broader cell therapy market definition, Towards Healthcare on current and long-term market estimates, Johnson & Johnson on Carvykti sales, Bristol Myers Squibb on Breyanzi sales, Gilead on Yescarta and Tecartus, Novartis on Kymriah, Iovance on Amtagvi, Vericel on MACI, Vertex on Casgevy, Autolus on Aucatzyl, and Mesoblast on Ryoncil.
Additional sources used to test access, treatment activity and future expansion include the FDA on removal of CAR-T REMS requirements, the EBMT activity report, Alliance for Regenerative Medicine's Q2 2026 sector dataset, ARM's approved-products database, Cabaletta Bio on rese-cel autoimmune data, Cellectis on its strategic exit from lasme-cel and eti-cel, Sana Biotechnology on suspended allogeneic CAR-T programs, and Legend Biotech on initial human LB2501 in vivo CAR-T results.

If you build or invest in the cell therapy market, you need to know which business models pay off now and which ones are fading. That's why our report covering it has a whole section on it.
Written by the New Market Pitch teamWe track new markets so founders and investors can move faster. About us